
Watch · 0:52
Trouble conceiving a second baby? Secondary infertility explained
Finding it hard to conceive a second baby? Secondary infertility explained: why it happens and what can help.
Get clear answers, and a plan
Assessment from ₹300
Indicative price for consultation and ultrasound. Your doctor advises which tests you need.
5.0★ 2,985+ Google reviews across our eight centres
If any of these sound familiar, a consultation is the right next step.
Book a Consultation
Conceiving needs healthy ovulation, open fallopian tubes, a receptive uterus and balanced hormones. A problem in any one can delay pregnancy, so the evaluation looks at all of them.
You leave with answers and a plan based on what was actually found.
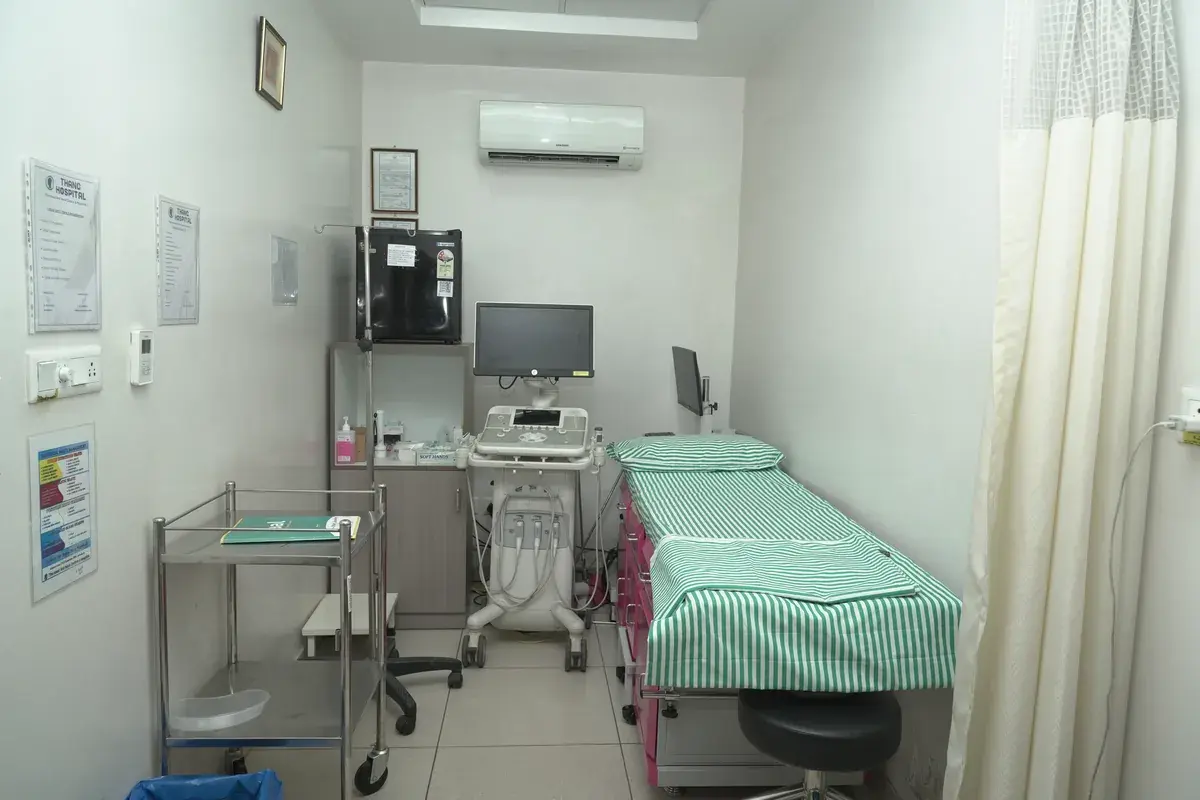
Most of the first steps are a conversation, an ultrasound and blood tests. We add other tests only when your results call for them.
Every Yaal centre has consulting rooms, ultrasound and blood sample collection.
Our eight Chennai centres:
Tube X-rays (HSG) are done at our Kilpauk centre.
Your treatment depends on the cause, and many causes have more than one option.
Treatment usually starts with ovulation induction.
Guide to PCOSTreating the thyroid can help restore regular cycles.
Guide to thyroidYour doctor explains the options, which may include IVF.
Guide to blocked tubesA plan that takes your AMH and age into account.
Low ovarian reserve careThe plan depends on severity and your fertility goals.
Guide to endometriosisNot all need removing. It depends on their size and position.
Guide to fibroidsWe look for the cause before you try again.
Recurrent pregnancy lossHigh-level prices to help you plan. Your doctor and clinic confirm the final cost based on your needs and the tests involved.
| Assessment, from | ₹300 |
| Fertility Blood Panel | ₹3,000 – ₹5,000 |
| Semen Analysis | ₹500 – ₹1,000 |
Prices are indicative and vary with the tests you need.
A detailed discussion of your menstrual history, prior pregnancies, surgeries, and general health to guide which tests are needed.
Blood tests including AMH, FSH, LH, thyroid function, and prolactin, alongside an antral follicle count on ultrasound, to assess ovulatory function and egg supply.
A transvaginal ultrasound to examine the ovaries, uterus, and uterine lining, and to look for fibroids, polyps, or ovarian cysts.
Where needed, an HSG X-ray at our Kilpauk centre checks that the fallopian tubes are open and the uterine cavity is normal.
Your results are reviewed together and used to build a treatment plan specific to what has actually been found, rather than a generic protocol.

MBBS, MS (OG), MRCOG (UK), FRM. Founder and Director of Yaal Fertility Centre, with 3,000+ IVF cycles supervised.
This page is for general information and is not a substitute for personal medical advice. Fertility treatment depends on individual circumstances, so please book a consultation to discuss your own case.
 Dr. Karthikha RaviMBBS, DGO, DNB (OG), MRCOG, FMAS, CIMP
 Dr. P. Lakshmi PriyaaMBBS, MS (OG), DNB (OG), FMAS
 Dr. Preethi MMBBS, MS (OG), DNB (OG), FMAS, FART
 Dr. Aiswarya RMBBS, MS (OG), DNB (OG), FRM
 Dr. P. PradeepaMBBS, MS (OG), Fellowship in Endogynaecology
 Dr. Anuvigashini MMBBS, MS (OG), DNB (OG), FRM
 Dr. Kunguma SangeethaMBBS, MS (OG), DNB (OG), FRM
 Dr. Nandhini G MMBBS, MS (OG), Certified in Clinical ART & Embryology
Real stories from families who found their path to parenthood at Yaal Fertility Centre.









We are extremely grateful to our Gynaecologist (Rukkayal Mam) for her exceptional care, patience, and constant encouragement throughout our journey. After few years of waiting and uncertainty, we were finally blessed with our Twin babies.
Suganya P
Fertility Treatment, Twins
via Google Reviews
Watch · 0:52
Trouble conceiving a second baby? Secondary infertility explained
Finding it hard to conceive a second baby? Secondary infertility explained: why it happens and what can help.
Female fertility depends on several systems working together: the ovaries must release a healthy egg on a regular schedule, the fallopian tubes must be open so sperm and egg can meet, the uterus must be able to receive and support a pregnancy, and the hormonal signalling that coordinates all of this must be intact. A problem in any one of these can be enough to prevent or delay conception: which is why a thorough evaluation looks at the whole system rather than assuming a single obvious cause.
The workup usually begins with a detailed history and a small set of blood tests and scans, and from there is guided by what those first results show. Ovulatory disorders, such as polycystic ovary syndrome (PCOS) and thyroid dysfunction, are among the most common and often the most treatable causes. Tubal factors: blockage or scarring of the fallopian tubes, frequently from prior infection or surgery: prevent egg and sperm from meeting. Uterine factors, including fibroids, polyps, adhesions, and congenital septae, can interfere with implantation even when ovulation and the tubes are normal. Diminished ovarian reserve and age-related decline in egg quantity and quality affect the chance of conception independently of any structural problem. Endometriosis can distort pelvic anatomy, affect egg quality, and impair implantation. And cervical factors occasionally play a role in how sperm travel from the vagina into the uterus.
Age deserves particular mention, because it is the single variable that cannot be corrected by treatment. Egg quantity and quality decline gradually through a woman’s thirties and more steeply after 35, and this decline is a biological fact rather than a reflection of health or lifestyle. It does not mean pregnancy is impossible: it means timelines matter, and it is one of the reasons we recommend a fertility evaluation sooner rather than later for women in their mid-to-late thirties.
At Yaal Fertility Centre, the female evaluation combines a hormone panel, ovarian reserve testing (AMH and antral follicle count), pelvic ultrasound, and, where indicated, a hysterosalpingogram (HSG) to assess the tubes and uterine cavity. Dr. Rukkayal Fathima uses these results to build a picture of exactly where the obstacle lies, so that treatment addresses the actual cause rather than a generic assumption about what “female infertility” means.
This page is an overview of that evaluation. Several of the conditions it touches on, including diminished ovarian reserve and recurrent pregnancy loss, are covered in more depth on their own pages, which your evaluation may lead you to.
Polycystic ovary syndrome (PCOS) is one of the most common causes of irregular or absent ovulation. It is a hormonal condition, not simply a matter of ovarian cysts, and it can present very differently between women: some with irregular cycles and few other symptoms, others with additional features such as acne, excess hair growth, or weight changes. The unifying problem for fertility is that eggs are not released on a predictable schedule, which makes natural conception harder to time and, in some cases, prevents ovulation altogether.
Thyroid dysfunction: both an underactive and an overactive thyroid: can disrupt the hormonal signalling that governs ovulation and menstrual regularity. It is checked routinely in the female fertility workup because it is common, easily tested for, and often very treatable with medication.
Both conditions are usually managed first with medical treatment aimed at restoring regular ovulation, with more advanced fertility treatment reserved for cases that do not respond or where other factors are also present.
Tubal factor infertility occurs when the fallopian tubes are blocked or scarred, most often as a result of prior pelvic infection, endometriosis, or previous pelvic or abdominal surgery. Because fertilisation normally happens inside the fallopian tube, a blockage can prevent sperm and egg from ever meeting, even when ovulation and the uterus are entirely normal. This is assessed with a hysterosalpingogram (HSG), which uses a small amount of contrast dye and an X-ray to check whether the tubes are open.
Uterine factors affect implantation rather than fertilisation. Fibroids are benign muscular growths in the uterine wall that can, depending on their size and location, distort the uterine cavity or interfere with implantation. Polyps are growths of the uterine lining that can similarly disrupt implantation. Adhesions (scar tissue within the uterine cavity) most often follow prior surgery or infection. A uterine septum is a congenital division of the uterine cavity present from birth. Many of these are correctable with minor surgical procedures once identified, which is why uterine assessment is a standard part of the workup rather than an optional extra.
Every woman is born with a fixed number of eggs, and that number declines steadily with age: it is not replenished. Ovarian reserve refers to the remaining quantity (and, indirectly, the quality) of a woman’s eggs, and it is estimated using a blood test for Anti-Müllerian Hormone (AMH) together with an antral follicle count on ultrasound.
Ovarian reserve declines gradually through the thirties and more steeply from the mid-to-late thirties onward, and this decline is a normal biological process rather than a sign of poor health. A lower-than-expected reserve for a woman’s age is described as diminished ovarian reserve, and it can occur earlier than expected due to genetics, prior ovarian surgery, chemotherapy, or for no identifiable reason at all.
Ovarian reserve testing does not simply confirm a diagnosis: it helps determine timelines. A woman with a lower reserve for her age may benefit from moving to more effective treatment sooner rather than waiting, since the window in which her own eggs remain viable is narrower than average. This topic, and the treatment options for diminished ovarian reserve specifically, are covered in more depth on our dedicated page.
Endometriosis occurs when tissue similar to the lining of the uterus grows outside it, most commonly on the ovaries, fallopian tubes, and pelvic lining. It can cause pain, particularly around periods, though some women have little or no pain despite significant disease, and it is diagnosed definitively by laparoscopy, though ultrasound and clinical history can raise strong suspicion beforehand.
Its effect on fertility varies with severity. Mild endometriosis may have little measurable impact, while more advanced disease can distort pelvic anatomy, damage the fallopian tubes, affect egg quality, and interfere with implantation. Management depends on severity and on how urgently a pregnancy is being pursued, and can range from surgical treatment to moving directly to IVF, which bypasses much of the anatomical disruption endometriosis can cause.
Bringing the pieces together, the standard evaluation typically includes:
Not every test is needed for every woman: the history and initial findings guide what is actually necessary. The goal throughout is to identify the specific obstacle to conception, so that the treatment that follows is targeted rather than generic.
The workup exists to answer one practical question: which treatment, out of a fairly wide range, actually fits what has been found? Rather than starting every couple on the same protocol, the findings above are used to place each woman on a treatment pathway that matches the specific obstacle identified.
Where the main issue is ovulatory: irregular or absent ovulation from PCOS or another cause, with open tubes and a normal uterine cavity: treatment usually starts with ovulation induction, paired with either timed intercourse or IUI depending on sperm parameters and how long lower-intensity treatment has already been tried. This is the least invasive route and, for the right diagnosis, often the most successful first step rather than a formality on the way to something else.
Where the workup instead points to tubal blockage, moderate-to-severe endometriosis, a significant male-factor issue, or unexplained infertility that has not responded to simpler treatment, moving more directly to IVF: with ICSI where sperm quality is a factor: is generally the more effective route, since it bypasses the specific obstacle rather than working around it indirectly. Uterine factors such as polyps, submucosal fibroids, or adhesions are often corrected surgically first, regardless of which fertility treatment follows, since an abnormal cavity can undermine an otherwise well-planned cycle.
Several of the causes this evaluation identifies have their own dedicated treatment pathway, which your evaluation may lead you to rather than staying on this page: diminished ovarian reserve has its own protocol considerations, PRP included, on our low ovarian reserve page; recurrent pregnancy loss has a dedicated investigation and management pathway; and PCOS and endometriosis management specifically, beyond the fertility-treatment ladder described here, are covered in depth on our women's health services pages. Dr. Rukkayal will tell you plainly which of these applies once your results are in, rather than leaving you to guess from a generic checklist.
Doctor-reviewed articles to help you prepare and decide

Discover what happens during a female fertility evaluation. Learn about hormone panels, pelvic ultrasounds, HSG, and how results guide your treatment plan.

Preparing for your first fertility consultation? Learn what medical history to bring, questions to ask, and how our Chennai specialists build your plan.

Understand the AMH test for ovarian reserve. Learn about normal ranges by age, low vs. high AMH levels, and how it impacts your IVF or IUI success.
Related treatments: IVF Treatment, IUI Treatment, ICSI Treatment, Recurrent Pregnancy Loss, Low Ovarian Reserve & PRP
Leave your number and we will book your assessment for the right day of your cycle.