
Kilpauk
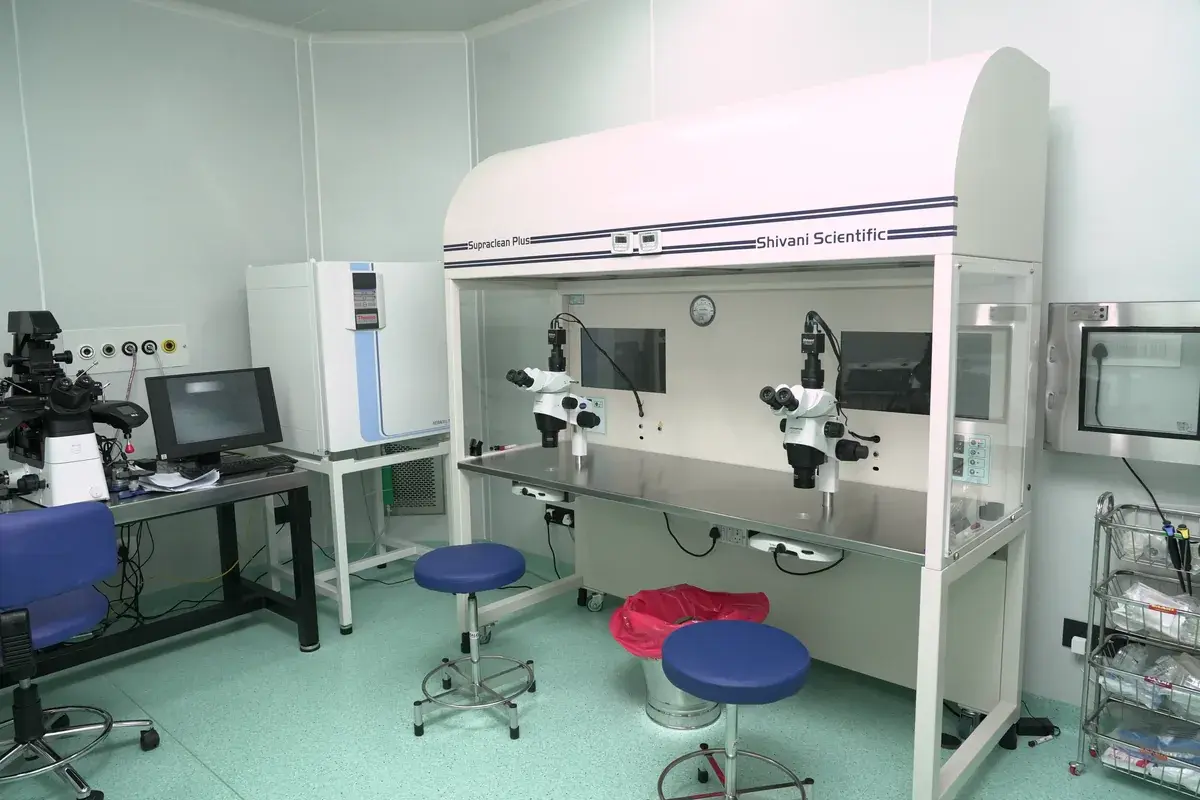
Central Chennai, near Kilpauk Metro. Our flagship hospital, with an embryology lab, operation theatres and recovery rooms.
No. 747, Poonamallee High Road, Alagappa Nagar, Kilpauk, Chennai – 600 010
One cycle, more chances
5.0★ 2,985+ Google reviews across our eight centres
Tests at all 8 centres. Embryo labs at: Kilpauk, Thiruvanmiyur, Velappanchavadi and Tambaram
If any of these sound familiar, a consultation is the right next step.
Book a Consultation
Embryo freezing stores good-quality embryos from an IVF cycle so they can be transferred later. It is a normal part of modern IVF.
It can mean a second chance without repeating stimulation and egg retrieval.
Your doctor explains whether freezing suits your cycle, how long embryos can be stored, and what happens next.
Consultations, scans and tests happen at all eight Yaal centres. Embryo freezing and storage happen at the four centres with an embryology lab.
Our eight Chennai centres:
Central Chennai, near Kilpauk Metro. Our flagship hospital, with an embryology lab, operation theatres and recovery rooms.
No. 747, Poonamallee High Road, Alagappa Nagar, Kilpauk, Chennai – 600 010
South Chennai, near ECR. An IVF centre with its own embryology lab, IVF theatre and recovery room.
Second Floor, No. 1, 3rd Street, Malaviya Avenue, Thiruvanmiyur, Chennai – 600 041
West Chennai, on Poonamallee High Road. An IVF centre with its own embryology lab, IVF theatre and recovery room.
2nd Floor, Dr. Mehta's Global Campus, No. 50, Poonamallee High Road, Velappanchavadi, Thiruverkadu, Chennai – 600 077
South Chennai, near Tambaram railway station. An IVF centre with its own embryology lab, operation theatres and in-patient rooms.
No. 4, Rajaji Road, West Tambaram, Tambaram, Chennai – 600 045
Your treatment depends on the cause, and many causes have more than one option.
Saves them for another attempt or another child.
IVF treatmentThe transfer can wait until your uterus is ready.
Frozen embryo transferEmbryos wait safely while results come back.
Genetic testingFollowing a standard IVF cycle, eggs are retrieved and fertilized. Embryos are cultured in our state-of-the-art embryology lab.
Our embryologists assess embryo quality. The best embryo(s) are selected for fresh transfer, and remaining high-quality embryos are prepared for freezing.
Embryos are frozen using vitrification: an ultra-rapid freezing technique that prevents ice crystal formation, achieving survival rates above 95%.
Frozen embryos are stored in liquid nitrogen tanks. When ready, they are thawed and transferred in a frozen embryo transfer (FET) cycle, which is simpler and less invasive than a full IVF cycle.

MBBS, MS (OG), MRCOG (UK), FRM. Founder and Director of Yaal Fertility Centre, with 3,000+ IVF cycles supervised.
This page is for general information and is not a substitute for personal medical advice. Fertility treatment depends on individual circumstances, so please book a consultation to discuss your own case.
 Dr. Karthikha RaviMBBS, DGO, DNB (OG), MRCOG, FMAS, CIMP
 Dr. P. Lakshmi PriyaaMBBS, MS (OG), DNB (OG), FMAS
 Dr. Preethi MMBBS, MS (OG), DNB (OG), FMAS, FART
 Dr. Aiswarya RMBBS, MS (OG), DNB (OG), FRM
 Dr. P. PradeepaMBBS, MS (OG), Fellowship in Endogynaecology
 Dr. Anuvigashini MMBBS, MS (OG), DNB (OG), FRM
 Dr. Kunguma SangeethaMBBS, MS (OG), DNB (OG), FRM
 Dr. Nandhini G MMBBS, MS (OG), Certified in Clinical ART & Embryology
Real stories from families who found their path to parenthood at Yaal Fertility Centre.









We are extremely grateful to our Gynaecologist (Rukkayal Mam) for her exceptional care, patience, and constant encouragement throughout our journey. After few years of waiting and uncertainty, we were finally blessed with our Twin babies.
Suganya P
Fertility Treatment, Twins
via Google Reviews
Embryo freezing: cryopreservation: is the storage of embryos created during an IVF cycle, so they can be transferred at a later date rather than discarded. It is not a side service or an optional extra; it is a core part of how modern IVF works.
A stimulated IVF cycle usually produces more than one good embryo. Only one is normally transferred, because transferring several risks a twin or triplet pregnancy, which carries real dangers for both mother and babies. That leaves surplus embryos: and freezing them is what turns a single, demanding IVF cycle into several chances at pregnancy.
The value of this is easy to underestimate. If a fresh transfer does not succeed, a frozen embryo from the same cycle can be transferred in a frozen embryo transfer (FET): a far simpler, cheaper, and gentler procedure that requires no ovarian stimulation, no egg retrieval, and no sedation. And if it does succeed, the remaining embryos are still there when you want a second child.
At Yaal Fertility Centre we use vitrification, an ultra-rapid freezing technique that cools embryos so quickly that damaging ice crystals cannot form. Survival rates on thawing exceed 95%: a decisive improvement over the older slow-freezing methods, and the advance that made frozen embryo transfer as reliable as it now is.
It once seemed self-evident that a fresh embryo transfer, transferring an embryo in the same cycle it was created, must be better than freezing and thawing. That assumption has not held up, and understanding why explains a great deal about modern IVF.
The problem with fresh transfer is the stimulation cycle itself. To produce multiple eggs, the ovaries are driven hard with hormone medication, and this leaves oestrogen levels far above what occurs in a natural cycle. Those hormone levels also act on the uterine lining, and in some women the endometrium is simply not in an ideal state to receive an embryo at that moment. The embryo may be excellent; the environment it is being placed into is not.
Frozen embryo transfer separates the two. The embryos are created and frozen; then, in a later cycle with no stimulation, the uterine lining is prepared carefully and unhurriedly, and the embryo is transferred when the endometrium is genuinely receptive. The embryo is no longer competing with the after-effects of stimulation.
The result is that FET success rates are comparable to fresh transfer, and in some situations exceed it. FET also carries a lower risk of ovarian hyperstimulation syndrome (OHSS), because pregnancy following a fresh transfer can worsen OHSS in a woman whose ovaries have over-responded: which is why women at high risk are often advised to freeze all embryos and transfer later.
This is not an argument that frozen is always better. It is an argument that freezing is not a compromise or a fallback. Dr. Rukkayal will recommend fresh or frozen transfer based on your response to stimulation, your OHSS risk, and the state of your endometrium: not on a blanket rule.
If you have been through a full IVF cycle, the most striking thing about a frozen embryo transfer is how much less it demands of you.
There is no ovarian stimulation. No high-dose hormone injections, no daily monitoring of follicle growth, no trigger shot. There is no egg retrieval. No sedation, no procedure, no recovery day. The embryos already exist.
What an FET cycle involves instead is preparing the uterine lining. This may be done in a natural cycle, tracking your own ovulation and timing the transfer accordingly, or with medication to build the endometrium in a controlled way. Which approach is used depends on whether your cycles are regular and on your history. You will have a small number of scans to confirm the lining has reached an appropriate thickness.
On the day, the chosen embryo is thawed, surviving in over 95% of cases, and transferred through a fine catheter into the uterus. The transfer takes a few minutes, requires no anaesthesia, and feels much like a smear test. You can go back to normal activity straight away; bed rest is not required and does not improve outcomes.
Then the same two-week wait as any transfer, ending with a beta-hCG blood test.
An FET is therefore substantially cheaper, physically gentler, and less disruptive than a full IVF cycle: which is precisely the point of having frozen embryos in the first place.
Embryos are stored in liquid nitrogen at around −196°C. At that temperature, biological activity effectively ceases: nothing is metabolising, nothing is ageing, nothing is deteriorating. An embryo stored for ten years is, biologically, in the same condition as the day it was frozen.
This is borne out in practice: pregnancy rates from embryos stored for many years are comparable to those stored briefly, and healthy babies have been born from embryos frozen for well over a decade. Duration in storage is not, in itself, a risk factor.
What matters far more than storage time is the age you were when the embryos were created. An embryo made when you were 32 remains a 32-year-old embryo, however long it sits in the tank. This is what makes freezing so valuable: it preserves the quality of that moment.
Storage is renewed annually, up to the 10-year limit set by Indian law, and there are practical and legal matters attached to it: consent, storage duration limits, and what happens to embryos you no longer intend to use. These are covered in the section below, and they are more consequential than most couples expect.
This is the part of embryo freezing that clinics tend to skip and that couples most wish they had understood at the outset. It deserves to be said clearly.
An embryo is created from both partners’ gametes, and both partners normally have a say in what happens to it. This is the fundamental difference between freezing embryos and freezing eggs. Frozen eggs remain solely yours, and you can later choose whom to have a child with. A frozen embryo already involves a specific partner: and consent from both parties is normally required to use it.
The implications only become apparent when circumstances change. If a couple separates, or if one partner withdraws consent, the embryos generally cannot be used by the other. This has been the subject of painful and well-publicised legal disputes elsewhere in the world, and it is not a hypothetical concern. Couples who freeze embryos while in a stable relationship rarely imagine that they might one day disagree about them.
There are also decisions you will eventually have to make about embryos you do not use. Broadly, the options are to continue storing them, to allow them to perish, to donate them to another couple, or to donate them to research: where permitted. Most couples find these decisions considerably harder than they expected, and it is common to defer them for years by continuing to pay storage fees.
None of this is a reason not to freeze embryos. It is a reason to discuss the consent forms properly rather than signing them in a hurry, and to know that if you are single, or unsure about your relationship, egg freezing may be the more appropriate choice precisely because it keeps that decision open.
Embryo storage and consent in India are governed by the ART (Regulation) Act, 2021. Our team will take you through exactly what you are consenting to before anything is frozen.
Doctor-reviewed articles to help you prepare and decide

Confused about embryo freezing vs egg freezing? Learn the key differences in success rates, processes, costs, and which option fits your fertility goals.

Discover the typical frozen embryo survival rate after thawing, key factors that influence survival, and how advanced vitrification protects your embryos.

Understand the frozen embryo transfer (FET) process. Learn about vitrification, natural vs. medicated cycles, timeline, and success rates in this expert guide.
Related treatments: IVF Treatment, ICSI Treatment, Genetic Testing (PGT), Frozen Embryo Transfer
Leave your number and we will call you back to talk through freezing your embryos.