
Kilpauk
Central Chennai, near Kilpauk Metro. Our flagship hospital, with an embryology lab, operation theatres and recovery rooms.
No. 747, Poonamallee High Road, Alagappa Nagar, Kilpauk, Chennai – 600 010
Choose your embryo with more confidence
5.0★ 2,985+ Google reviews across our eight centres
Tests at all 8 centres. IVF labs at: Kilpauk, Thiruvanmiyur, Velappanchavadi and Tambaram
If any of these sound familiar, a consultation is the right next step.
Book a Consultation
Preimplantation genetic testing (PGT) checks embryos from an IVF cycle before transfer. A few cells are analysed, and your doctor uses the results to help choose an embryo.
It lowers some risks, but no test can guarantee a healthy baby, and not everyone needs it.
PGT is used only to check for medical conditions. Choosing a baby's sex is illegal in India, and we never do it.
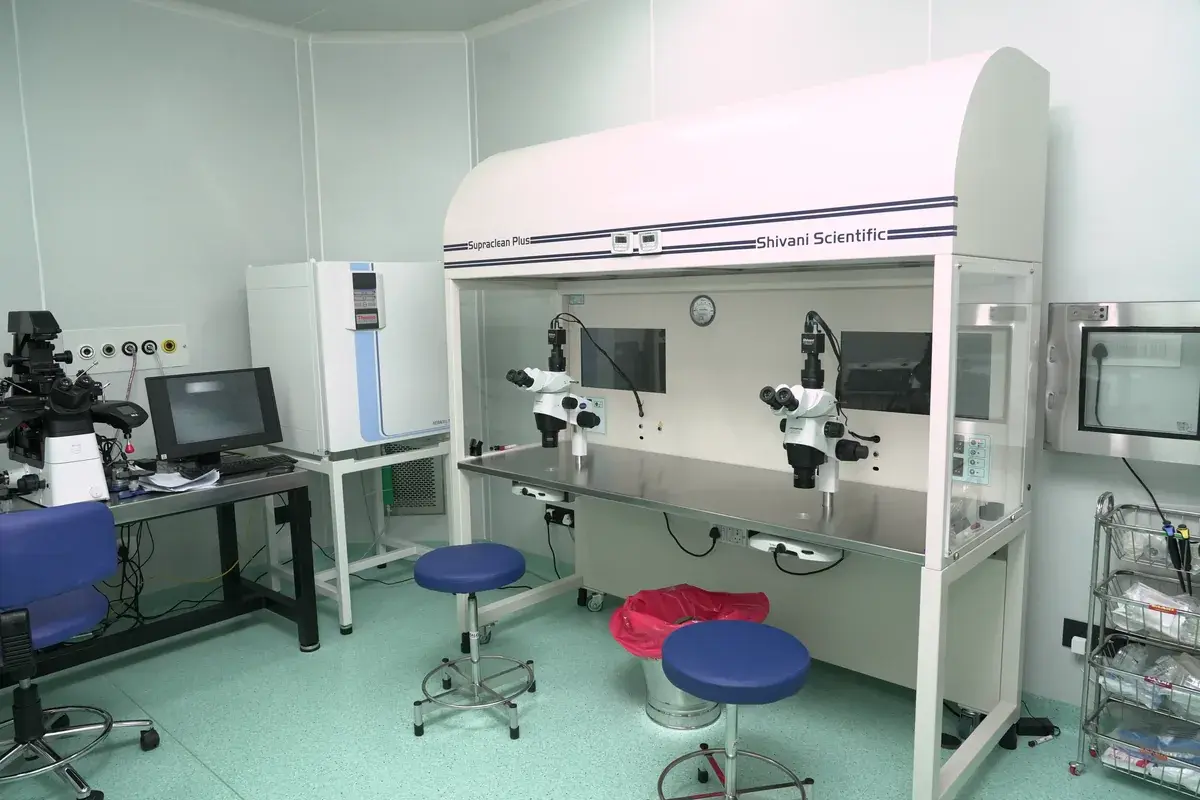
We review your history and family background, then explain which test would help, if any.
Consultations, scans and tests happen at all eight Yaal centres. Embryo biopsy and IVF happen at the four centres with an embryology lab.
Our eight Chennai centres:
Central Chennai, near Kilpauk Metro. Our flagship hospital, with an embryology lab, operation theatres and recovery rooms.
No. 747, Poonamallee High Road, Alagappa Nagar, Kilpauk, Chennai – 600 010
South Chennai, near ECR. An IVF centre with its own embryology lab, IVF theatre and recovery room.
Second Floor, No. 1, 3rd Street, Malaviya Avenue, Thiruvanmiyur, Chennai – 600 041
West Chennai, on Poonamallee High Road. An IVF centre with its own embryology lab, IVF theatre and recovery room.
2nd Floor, Dr. Mehta's Global Campus, No. 50, Poonamallee High Road, Velappanchavadi, Thiruverkadu, Chennai – 600 077
South Chennai, near Tambaram railway station. An IVF centre with its own embryology lab, operation theatres and in-patient rooms.
No. 4, Rajaji Road, West Tambaram, Tambaram, Chennai – 600 045
Your treatment depends on the cause, and many causes have more than one option.
Can help identify chromosomally normal embryos.
Recurrent pregnancy lossMay help in some cases, and your doctor reviews this first.
Why IVF cycles failPGT-M looks for that specific condition.
Carrier screeningDetailed consultation to understand your genetic history, discuss which type of PGT is appropriate (PGT-A, PGT-M, or PGT-SR), and set realistic expectations.
Standard IVF cycle with egg retrieval and fertilization. Embryos are cultured to the blastocyst stage (Day 5-6) for optimal biopsy.
A few cells are carefully removed from each blastocyst (trophectoderm biopsy) and sent for genetic analysis. Embryos are frozen during testing.
Results typically available in 2-3 weeks. Genetically normal embryos are identified, and the best embryo is transferred in a subsequent frozen embryo transfer cycle.

MBBS, MS (OG), MRCOG (UK), FRM. Founder and Director of Yaal Fertility Centre, with 3,000+ IVF cycles supervised.
This page is for general information and is not a substitute for personal medical advice. Fertility treatment depends on individual circumstances, so please book a consultation to discuss your own case.
 Dr. Karthikha RaviMBBS, DGO, DNB (OG), MRCOG, FMAS, CIMP
 Dr. P. Lakshmi PriyaaMBBS, MS (OG), DNB (OG), FMAS
 Dr. Preethi MMBBS, MS (OG), DNB (OG), FMAS, FART
 Dr. Aiswarya RMBBS, MS (OG), DNB (OG), FRM
 Dr. P. PradeepaMBBS, MS (OG), Fellowship in Endogynaecology
 Dr. Anuvigashini MMBBS, MS (OG), DNB (OG), FRM
 Dr. Kunguma SangeethaMBBS, MS (OG), DNB (OG), FRM
 Dr. Nandhini G MMBBS, MS (OG), Certified in Clinical ART & Embryology
Real stories from families who found their path to parenthood at Yaal Fertility Centre.









We are extremely grateful to our Gynaecologist (Rukkayal Mam) for her exceptional care, patience, and constant encouragement throughout our journey. After few years of waiting and uncertainty, we were finally blessed with our Twin babies.
Suganya P
Fertility Treatment, Twins
via Google Reviews
Watch · 0:38
Who decides your baby's traits, mom or dad?
A short look at how both parents shape a baby's traits through the genes they pass on.
Preimplantation Genetic Testing (PGT) is the genetic screening of embryos created during an IVF cycle, carried out before any embryo is transferred to the uterus. A few cells are removed from each embryo and analysed, so that the embryo selected for transfer is one already known to be genetically normal.
The reason this matters is that chromosomal abnormality in the embryo is the single most common cause of IVF failure and of early miscarriage. An embryo can look perfect under the microscope, well-formed, dividing on schedule, graded highly by an embryologist, and still carry the wrong number of chromosomes. Such an embryo will usually fail to implant, or will implant and then miscarry. Appearance alone cannot detect this; only genetic testing can.
The proportion of embryos affected rises sharply with maternal age, which is why PGT is most often discussed with women over 35, with couples who have had repeated IVF failure, and with couples who have suffered recurrent pregnancy loss.
PGT is not one test but three, used for different purposes: PGT-A for chromosome number, PGT-M for a specific inherited single-gene disorder, and PGT-SR for structural chromosomal rearrangements. They are explained below, because choosing the right one depends entirely on what you are trying to find.
PGT is always performed within an IVF cycle. It cannot be done in natural conception, because there is no embryo outside the body to test.
These three tests share a technique but answer entirely different questions. Choosing between them is not a matter of preference: it depends on what, specifically, you have reason to look for.
PGT-A (Aneuploidy) counts chromosomes. A normal embryo has 46; an aneuploid embryo has too many or too few, and most such embryos either fail to implant or miscarry. Some, such as an extra chromosome 21, result in a live birth with a chromosomal condition: in that case, Down syndrome. PGT-A does not look for any particular inherited disease; it simply checks that the count is right. This is the test used when the concern is age-related chromosomal risk, repeated IVF failure, or recurrent miscarriage, and it is by far the most commonly performed.
PGT-M (Monogenic) looks for one specific single-gene disorder that the parents are known to carry: thalassemia, cystic fibrosis, sickle cell disease, spinal muscular atrophy and others. It is not a screen. It is a targeted search for a known mutation in a family, and it can only be performed when that mutation has already been identified through prior genetic testing of the parents. For carrier couples who face a recurring risk of passing on a serious inherited condition, PGT-M is the reason to consider IVF even when fertility is otherwise normal.
PGT-SR (Structural Rearrangements) is for people who carry a balanced chromosomal rearrangement, such as a translocation or inversion. A carrier is typically healthy, all the genetic material is present, just arranged differently, but the embryos they produce can inherit an unbalanced amount of it, causing miscarriage or a child with serious abnormalities. PGT-SR identifies the embryos that have inherited a balanced or normal arrangement.
Getting this right is precisely why genetic counselling comes before treatment, not after. The counselling session determines which test is appropriate, whether it is appropriate at all, and what it can and cannot tell you.
PGT adds cost and complexity to an IVF cycle, and it is not right for everyone. Being honest about who benefits is more useful than presenting it as a universal upgrade.
PGT is most clearly worthwhile when:
PGT is less likely to help when: you are young, have a good ovarian reserve, and are producing several good-quality embryos in your first cycle. In that situation many of your embryos are likely to be normal anyway, and testing adds cost, a biopsy, and a delay: while the embryo you would have transferred first may well have been the one PGT would have chosen.
There is also an uncomfortable scenario to acknowledge: if you produce only one or two embryos and testing shows them to be abnormal, you will have no embryo to transfer at all. The information is real and it is worth having: but it can end a cycle that would otherwise have proceeded in hope. That is a trade-off you should make knowingly rather than discover afterwards.
Dr. Rukkayal will tell you honestly whether PGT is likely to help in your specific case, rather than recommending it by default.
The concern almost every couple raises is the obvious one: you are taking cells out of my embryo: will that harm the baby? It is the right question, and the answer depends on when and where the cells are taken.
The biopsy is performed at the blastocyst stage, on day 5 or 6 of embryo development. By this point the embryo has already differentiated into two distinct parts: an inner cell mass, which goes on to become the baby, and an outer layer called the trophectoderm, which goes on to become the placenta.
The biopsy takes a few cells from the trophectoderm, the future placenta, and does not touch the inner cell mass. This is the entire basis of its safety, and it is why the timing matters so much. Biopsy at this stage is well established, and studies have not shown an increased risk of birth defects.
Because results take two to three weeks to come back, the embryos are vitrified (flash-frozen) while testing proceeds. The transfer therefore happens in a later frozen embryo transfer cycle rather than fresh. This is not a drawback: frozen transfer also allows the uterine lining to be prepared optimally, without the hormonal effects of a stimulation cycle.
Two limitations should be stated. The biopsy samples a handful of cells, not the whole embryo, and in rare cases an embryo can contain a mix of normal and abnormal cells (mosaicism), which can make a result ambiguous. And no genetic test is 100% accurate: PGT dramatically reduces risk, but it does not reduce it to zero, and it is not a substitute for the antenatal screening you would have in any pregnancy.
PGT is frequently oversold, and it is worth being precise about its boundaries.
What PGT can do: identify embryos with the wrong number of chromosomes; identify embryos carrying a specific single-gene disorder that you are known to carry; identify embryos that have inherited an unbalanced chromosomal rearrangement; and thereby improve the chance that the embryo transferred will implant and result in a healthy live birth, while reducing the risk of miscarriage. That is a substantial and genuine benefit, and it is reflected in the success rates on this page.
What PGT cannot do:
Understood correctly, PGT is a selection tool, not a creation tool. It helps you transfer the best embryo you have. It cannot give you a better one than you have.
Doctor-reviewed articles to help you prepare and decide
Understand PGT, PGD, and PGS embryo genetic testing. Learn how embryo screening works, who it helps, and key benefits during your IVF journey.

Carrier screening is a blood test that shows if you silently carry a gene for an inherited condition. It matters when both partners carry the same one.

The AZF microdeletion test is a blood test for missing Y chromosome genes in men with zero or very low sperm. AZFc often still has sperm; AZFa/b usually not.
Related treatments: IVF Treatment, ICSI Treatment, Premarital Health Checkup, Recurrent Pregnancy Loss
Leave your number and we will book a genetic counselling session.